


Interstitial lung disease (ILD) is the most common pulmonary affection of rheumatoid arthritis (RA). Patients with a severe RA-ILD extent i.e. >20% according to chest Computed Tomography (CT) semiquantitative (SQCT) scores, have poor prognosis. Quantitative CT (QCT) assessment with operator independent methods based on free software represents a reliable solution already tested in other ILD related to rheumatic diseases.
ObjectivesThe main objective of this monocentric study is to verify if in RA-ILD there is a correlation between QCT and SQCT performed by experienced radiologists. Secondary aims are: (a) to explore if there is a difference of QTC indexes (QCTi) in RA-ILD patients with severe vs mild ILD extent; (b) to evaluate the discriminative ability of QCT in identifying severe RA-ILD patients.
Materials and methodsThe chest CTs of consecutive RA-ILD underwent to a SQCT assessment by two experienced chest radiologists. All CTs were also blindly post-processed by a rheumatologist in order to obtain the QCTi. QCTi correlations, distribution and discriminative ability were, respectively, verified using Spearman rank test, Mann–Whitney test and ROC curves.
ResultsThe majority of QCTi showed a moderate degree (0.40<r<0.59) with SQCT assessment (p-value<0.01). Patients with severe and mild ILD had dissimilar QCTi values (p=0.001). Almost all of QCTi had a good discriminative ability (AUC from 0.73 to 0.81, p-value=0.0001).
ConclusionsThese preliminary findings suggest that RA-ILD extent is related to QCTi. Moreover, QCTi can discriminate very well patients with a severe ILD. So, QCTi may become simple tools quickly estimate RA-ILD prognosis.
La enfermedad pulmonar intersticial (EPI) es la afección pulmonar más común de la artritis reumatoide (AR). Los pacientes con una extensión grave de EPI-AR, es decir, >20% según las puntuaciones semicuantitativas (SQCT) de la tomografía computarizada (TC) de tórax, tienen un pronóstico malo. La evaluación de la TC cuantitativa (QCT) con métodos independientes del operador basados en software libre, representa una solución confiable ya probada en otras EPI relacionadas con enfermedades reumáticas.
ObjetivosEl objetivo principal de este estudio monocéntrico es verificar si en la EPI-AR existe una correlación entre la QCT y la SQCT realizada por radiólogos experimentados. Los objetivos secundarios son: a) explorar si hay una diferencia de los índices QTC (QCTi) en pacientes con EPI-AR con extensión grave frente a leve; b) evaluar la capacidad discriminativa de la QCT para identificar pacientes con EPI-AR grave.
Materiales y métodosLas TC de tórax de EPI-AR consecutivas se sometieron a una evaluación SQCT por dos radiólogos torácicos experimentados. Todas las TC también fueron posprocesadas ciegamente por un reumatólogo para obtener el QCTi. Las correlaciones, la distribución y la capacidad discriminativa del QCTi se verificaron, respectivamente, mediante la prueba de rangos de Spearman, la prueba de Mann-Whitney y las curvas ROC.
ResultadosLa mayoría de los QCTi mostraron un grado moderado (0,40<r<0,59) con la evaluación de SQCT (valor p <0,01). Los pacientes con EPI grave y leve tuvieron valores de QCTi diferentes (p=0,001). Casi todos los QCTi tuvieron una buena capacidad discriminativa (AUC de 0,73 a 0,81, valor p=0,0001).
ConclusionesEstos hallazgos preliminares sugieren que la extensión de la EPI-AR está relacionada con el QCTi. Además, el QCTi puede discriminar muy bien a los pacientes con una EPI grave. Por lo tanto, el QCTi puede convertirse en herramientas simples para estimar rápidamente el pronóstico de la EPI-AR.
Rheumatoid arthritis (RA) is the most common inflammatory arthritis of unknown origin and poorly understood pathogenesis, including genetic susceptibility and environmental factors, affecting approximately 1% of the population in developed countries.1 Although the principal target of disease are the joins, the RA is considered a systemic disease, due to numerous extra-articular manifestations.2 The interstitial lung disease related to RA (RA-ILD) is the most frequent pulmonary involvement, with an estimated prevalence of 19–56%, depending on criteria for diagnosis as well as the method and frequency of radiographic imaging.3 Although there have been significant improvements in prognosis over the past 25 years, ILD remains the second leading cause of death in RA patients, following cardiovascular complications.4
High-resolution chest computer tomography (HRCT) is currently considered the gold standard imaging modality in confirming a diagnosis of RA-ILD.5 It also allows for the discrimination and estimation of the extension of the ILD, it can establish prognosis and guide treatment decisions.6
According to this background, visual scores and semiquantitative CT (sQCT) assessment, can estimate ILD extension, in terms of limited or extensive disease.7,8 sQCT assessment proposed by Goh and colleagues proves extremely useful because, as well as in other interstitial diseases associated with rheumatological diseases, it has an excellent prognostic value.9 Humphries et al., in 2 cohorts of patients with RA-ILD, showed quantitative assessment of lung fibrosis on CT imaging was associated with worse lung function at baseline and risk of mortality.10 On the other hand, Oh et al. demonstrate that a quantitative lung fibrosis analysis might be useful for predicting prognosis in patients with RA-ILD,11 and Karadag et al. stated that quantitative CT metrics demonstrated strong correlations with traditional scoring systems.12 However, sQCT assessment suffers from intra- and inter-observer variability.8
Quantitative CT (QCT) analysis is a promising tool to assess primary or secondary ILD and its extension. It is based on software providing highly accurate and operator-independent measurements, termed QCT indices (QCTi),13 which have been rapidly developed and validated in specific clinical settings, including systemic autoimmune diseases.14–17 To the best of our knowledge there are only few studies focused on the use of QCT in RA-ILD, mainly based on in-house software18 or as comparison with idiopathic pulmonary fibrosis.19
Herein, we designed a study to evaluate whether QCTi are of useful to detect the extent and severity of RA-ILD and to appraise differences between limited and extensive ILD.
MethodsThis is a retrospective study of patients with RA according to the ACR 87 or ACR/EULAR 2010 criteria; evaluated and managed at the interstitial lung diseases and rheumatology unit (ILD&RU), at the Instituto Nacional de Enfermedades Respiratorias, Ismael Cosio Villegas. The following inclusion criteria were applied: diagnosis of RA following 2010 ACR/EULAR classification criteria, ILD detectable at the chest CT scan obtained during the admission in the center, and age older than 18 years. The exclusion criteria included: incomplete patients’ files, refusal of participate to study, impossibility to contact patient. The research protocol was approved by the local ethics (ethics approval number C20-14) committees and was conducted in accordance with the Helsinki Declaration, and informed consent was signed from each patient included in the study. Patients data were retrospectively recorded by clinical files for: age, sex, disease duration, smoke habit, presence of rheumatoid factor and anti- citrullinated protein antibodies (ACPA). Tender and swollen joint and CDAI were registered at admittance at pneumology center. Functional lung parameters (FVC, FEV1, TLC DLCO) were performed during the hospitalization and between 3 months to TC execution; in all cases, the final diagnosis of RA-associated interstitial lung disease (RA-ILD) was established through a multidisciplinary discussion after excluding infection, drug toxicity, occupational exposures, sarcoidosis, smoking-related lung diseases, and malignancy.
HRTC chest scans performed during the hospitalization were assessed by two experienced chest radiologists (MS and AC) independently and blinded, these experts resolved any discrepancies by consensus after excluding infection, drug toxicity, occupational exposures, sarcoidosis, smoking-related lung diseases, and malignancy, concordance between the two expert radiologists was high for each of the characteristics evaluated20; recording the detectable ILD according to the semiquantitative score proposed by Goh et al.21 An ILD extent < and >20% were considered limited and extensive, respectively.
For CT analysis, a DICOM (Digital Imaging and Communications in Medicine) viewer and open-source software (Horos, www.horosproject.org) were used. All chest high-resolution CT scans underwent post-processing to obtain the following QCTi: kurtosis (Kurt), mean pulmonary attenuation (MLA), skewness (Skew), and standard deviation (Sdev). MLA and standard deviation represent the arithmetic mean and standard deviation of all these values, respectively. Kurtosis and skewness are other mathematical measures; however, they are dimensionless and describe the distribution of pulmonary attenuation values (kurtosis describes the “similarity” to a normal distribution, while skewness describes the symmetry of the distribution itself). The entire procedure, including the lung segmentation algorithm, was performed as previously described.22 Accordingly, the region of interest between −950HU and 400HU was considered as ‘pulmonary parenchyma’ (namely, lung parenchyma without vessels or bronchioles and not affected by fibrosis). Those voxels included in the whole lung volume with higher HU values were identified as non-parenchymal structures. The QTCi were calculated according to these definitions, as parenchymal (i.e., pKurt, pSkew, etc.) and total (i.e., tKurt, tSkew, etc.) QTC.
All CT images were centrally and blindly reviewed by the same board-certified radiologist (MS, NS) (Radiology Department, Azienda Ospedaliero-Universitaria di Parma) and QCT indices were then calculated. RA-ILD was defines as limited if 20% of pulmonary parenchima was affected, diffuse if >20% was affected. The SQCT assessment was carried out to calculate both Goh and Taouli scores for each CT scan.
Statistical analysisData were reported as mean and standard deviation (SD) for continuous variables and numbers and percentages for categorical variables. The Kolgomorov–Smirnov test was used to check the assumption of normality of the continuous variables. Differences between subgroups were analyzed using non-parametric tests, as appropriate. The Spearman rank test was used to determine correlations of QCT indices with SQCT scores, pulmonary function tests, and the other collected variables. A two-tailed probability of p<0.05 was considered statistically significant. All analyses were conducted using SPPS 20.0 (Chicago, IL, USA) and R (version 3.5.2) statistical software package (http://www.R-project.org/) (Vienna, Austria).
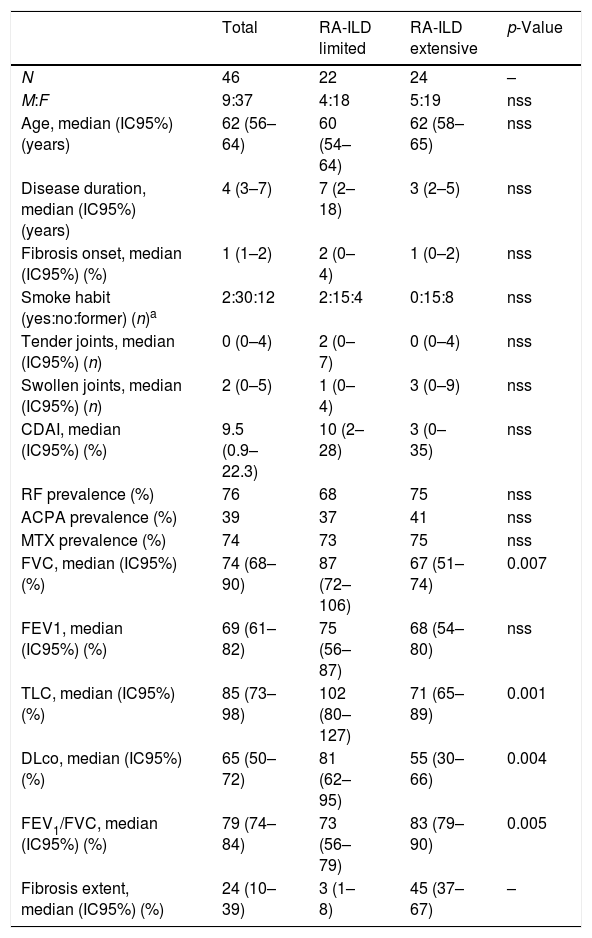
ResultsA total of 46 patients were retrospectively enrolled in the present study. Demographic characteristics of the participants are showed in Table 1. All patients included in the protocol presented ILD. Twenty-two patients (48%) were defined as having limited ILD, and 24 (52%) were defined having extensive ILD. Age, sex, disease duration, fibrosis onset, smoke habit, CDAI, RF, ACPA positivity and use of methotrexate were not significant different in the two groups enrolled. All parameters related to pulmonary function showed statistically significant differences; with the exception of FEV1. As expected, the sQCT score was far less in limited (3%; 1–8%) vs extensive (45%; 37–67%) RA-ILD (Table 1).
Clinic characteristics of the cohort and subgroups.
| Total | RA-ILD limited | RA-ILD extensive | p-Value | |
|---|---|---|---|---|
| N | 46 | 22 | 24 | – |
| M:F | 9:37 | 4:18 | 5:19 | nss |
| Age, median (IC95%) (years) | 62 (56–64) | 60 (54–64) | 62 (58–65) | nss |
| Disease duration, median (IC95%) (years) | 4 (3–7) | 7 (2–18) | 3 (2–5) | nss |
| Fibrosis onset, median (IC95%) (%) | 1 (1–2) | 2 (0–4) | 1 (0–2) | nss |
| Smoke habit (yes:no:former) (n)a | 2:30:12 | 2:15:4 | 0:15:8 | nss |
| Tender joints, median (IC95%) (n) | 0 (0–4) | 2 (0–7) | 0 (0–4) | nss |
| Swollen joints, median (IC95%) (n) | 2 (0–5) | 1 (0–4) | 3 (0–9) | nss |
| CDAI, median (IC95%) (%) | 9.5 (0.9–22.3) | 10 (2–28) | 3 (0–35) | nss |
| RF prevalence (%) | 76 | 68 | 75 | nss |
| ACPA prevalence (%) | 39 | 37 | 41 | nss |
| MTX prevalence (%) | 74 | 73 | 75 | nss |
| FVC, median (IC95%) (%) | 74 (68–90) | 87 (72–106) | 67 (51–74) | 0.007 |
| FEV1, median (IC95%) (%) | 69 (61–82) | 75 (56–87) | 68 (54–80) | nss |
| TLC, median (IC95%) (%) | 85 (73–98) | 102 (80–127) | 71 (65–89) | 0.001 |
| DLco, median (IC95%) (%) | 65 (50–72) | 81 (62–95) | 55 (30–66) | 0.004 |
| FEV1/FVC, median (IC95%) (%) | 79 (74–84) | 73 (56–79) | 83 (79–90) | 0.005 |
| Fibrosis extent, median (IC95%) (%) | 24 (10–39) | 3 (1–8) | 45 (37–67) | – |
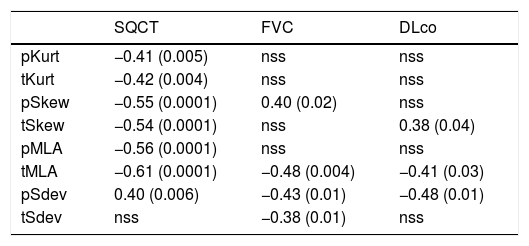
The correlation analysis showed that almost all parameters had significant correlation between QCTi, especially with tMLA with a negative correlation (−0.61) and pSdev where the correlation was positive (0.4)(see Table 2). On the other hand, FVC had statistically significant negative correlations with tMLA (−0.48), pSdev (−0.43) and tSdev (−0.38); while for pSkew the correlation was positive and significant (0.40). In the case of DLco, it had negative correlations with tMLA (−0.41) and pSdev (−0.48); and a positive correlation with tSkew (0.38).
Correlations of QCT, FVC and DLco indices (Spearman's rho and p-value).
| SQCT | FVC | DLco | |
|---|---|---|---|
| pKurt | −0.41 (0.005) | nss | nss |
| tKurt | −0.42 (0.004) | nss | nss |
| pSkew | −0.55 (0.0001) | 0.40 (0.02) | nss |
| tSkew | −0.54 (0.0001) | nss | 0.38 (0.04) |
| pMLA | −0.56 (0.0001) | nss | nss |
| tMLA | −0.61 (0.0001) | −0.48 (0.004) | −0.41 (0.03) |
| pSdev | 0.40 (0.006) | −0.43 (0.01) | −0.48 (0.01) |
| tSdev | nss | −0.38 (0.01) | nss |
Statistical correlations between QCTi parameters QCTi: (Kurtosis (Kurt), mean pulmonary attenuation (MLA), skewness (Skew), and standard deviation (Sdev)) and clinical parameters (FVC: Forced Vital Capacity; DLco: Pulmonary diffusing capacity of carbon monoxide.).
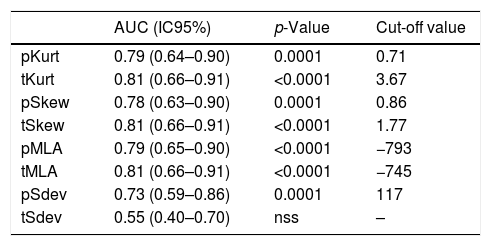
Regarding discriminative ability, with the exception of tSdev, all parameters were significant; tKurt, tSkew, and tMLA had the highest AUC values (0.81); the first two with positive cutoff points (3.67 and 1.77, respectively), while tMLA had a negative cutoff point (−745). Therefore, all QCTi assays showed significant discriminative ability for extended fibrosis, except for tSdev. Among the QCTi assays, tKurt showed the best discriminative ability (AUC=0.81; 95% CI: 0.65–0.91; p-value<0.0001) (Table 3).
Discriminatory ability of QCT indices for extensive fibrosis.
| AUC (IC95%) | p-Value | Cut-off value | |
|---|---|---|---|
| pKurt | 0.79 (0.64–0.90) | 0.0001 | 0.71 |
| tKurt | 0.81 (0.66–0.91) | <0.0001 | 3.67 |
| pSkew | 0.78 (0.63–0.90) | 0.0001 | 0.86 |
| tSkew | 0.81 (0.66–0.91) | <0.0001 | 1.77 |
| pMLA | 0.79 (0.65–0.90) | <0.0001 | −793 |
| tMLA | 0.81 (0.66–0.91) | <0.0001 | −745 |
| pSdev | 0.73 (0.59–0.86) | 0.0001 | 117 |
| tSdev | 0.55 (0.40–0.70) | nss | – |
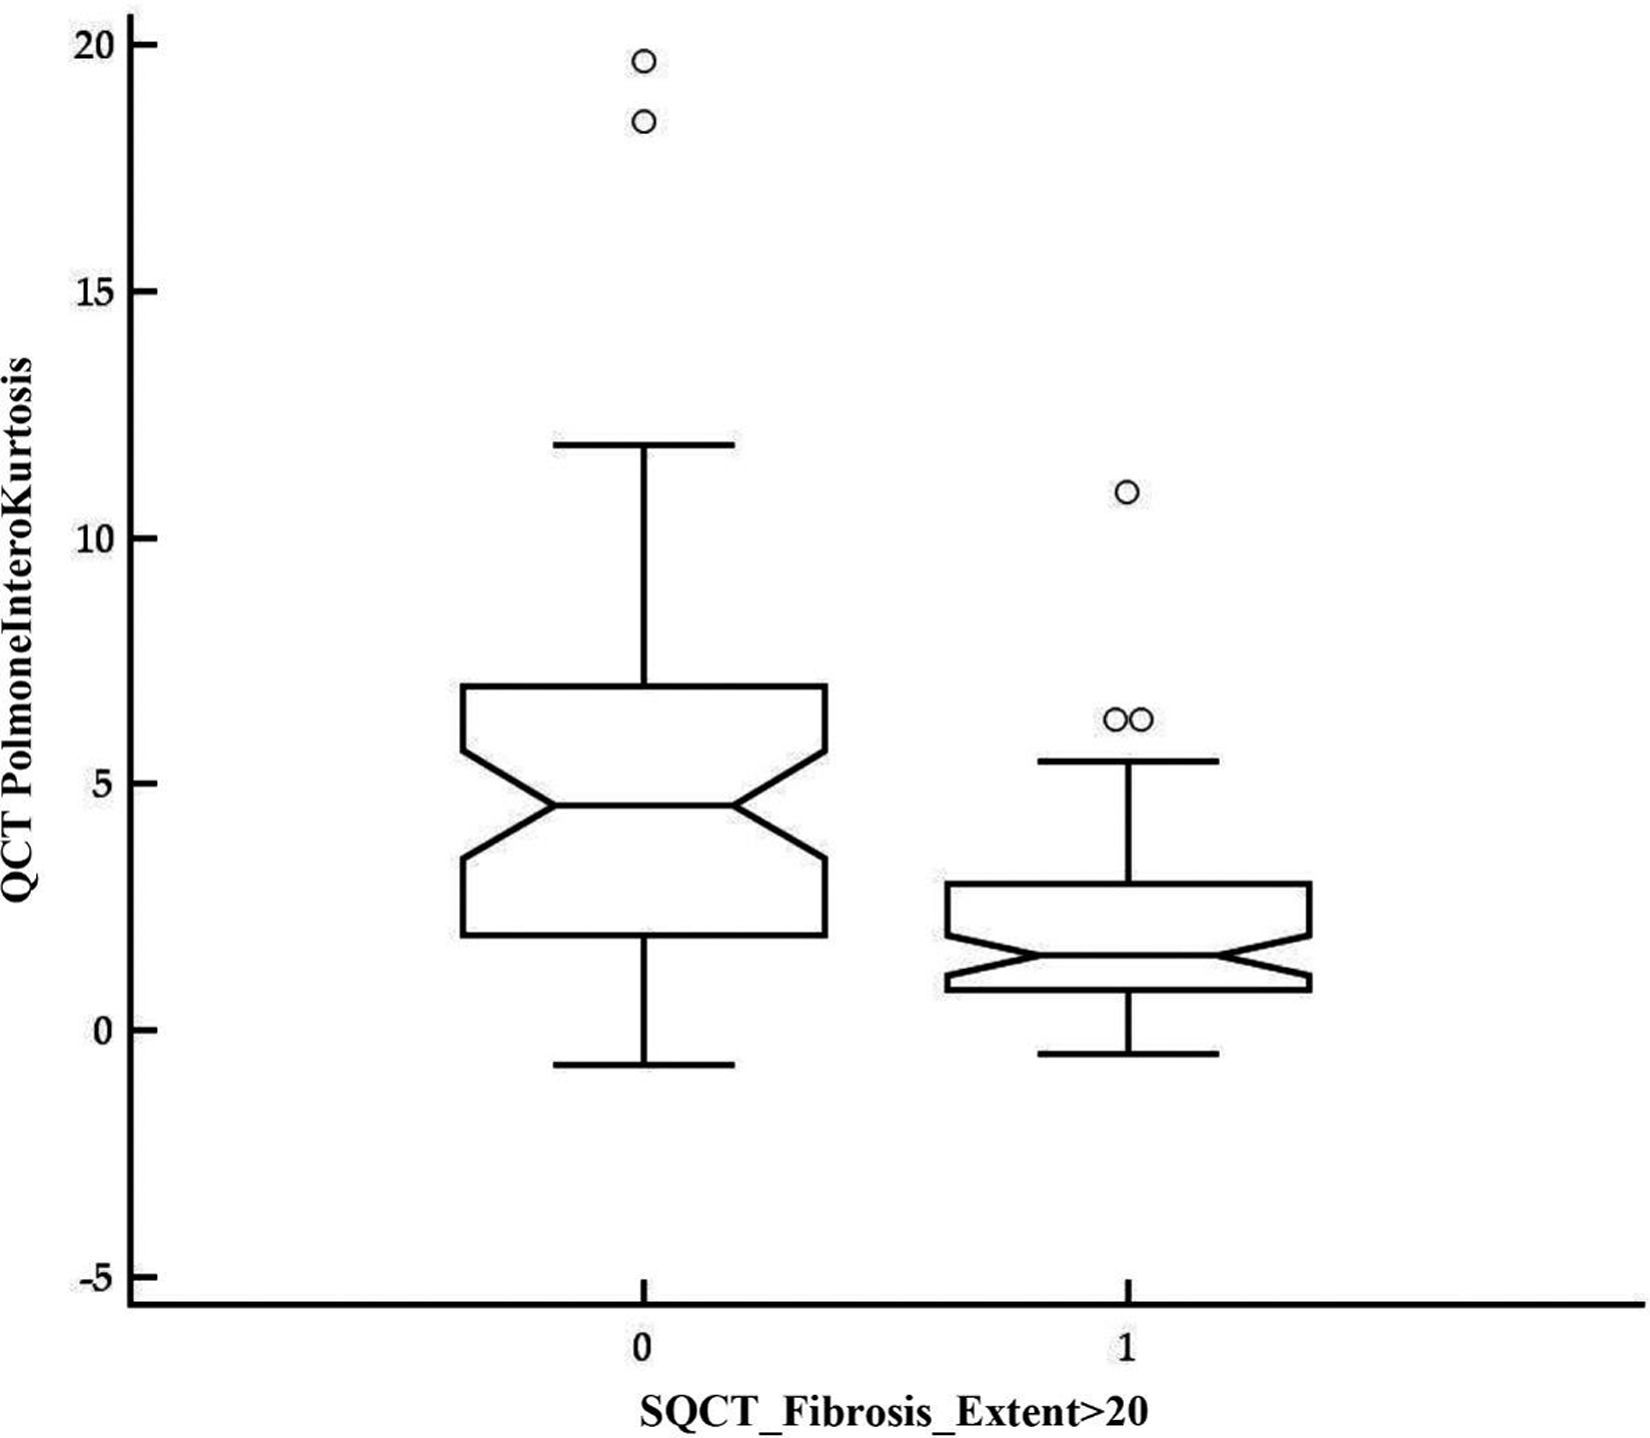
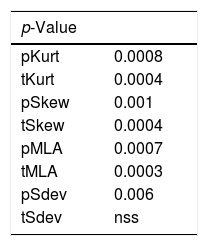
Finally, patients with limited and extensive RA-ILD presented different QCTi values (p<0.001), except for Sdev. In Fig. 1, notched box plots show the difference in the tKurt distribution between the aforementioned subgroups. Table 4 shows the p-values for the indices.
Although RA is considered a prevalent joints disease, extra-articular manifestations affect 40% of patients, and, between these, lung involvement is frequent, affecting serosal, airway, and/or parenchymal tissue. Other than frequent, RA-ILD affects seriously the prognosis of RA patient, representing the most common pulmonary cause of death and a significant contributor to morbidity (i.e. congestive heart failure represents the principal cause of premature death in RA patients.23
Prevalence and incidence of RA-ILD depends on diagnostic tools, varying from 5% detected in chest plain radiographs and one third of advanced cases in autopsy.24 Bongartz et al. evaluated a large cohort of RA patients over a mean follow up period of 16.4 years. The estimated prevalence of ILD was between 4 and 7.9% with 10, 20 and 30 year cumulative incidence of 3.5%, 6.3% and 7.7% respectively.25 Olson et al. reported the prevalence of clinically significant ILD to be approximately 6.8% in women and 9.8% in men.26
Differently of ILD associated to other autoimmune disease, RA-ILD presents often with a UIP pattern, mimic the primitive fibrosis of lung, with a very poor prognosis. Quantitative imaging has become a promising tool for the diagnosis, classification, and prognosis of ILD. Both global and regional lung abnormalities can be objectively and reproducibly measured using quantitative imaging, which is particularly useful for early disease assessment and the evaluation of subtle changes. Accurate classification of ILD and the identification of discrete changes allow for more personalized treatment decisions and, ultimately, improved patient outcomes. Since CT is the primary imaging modality for evaluating ILD, most computer-assisted support systems have been developed for this modality and are referred to as quantitative CT. While quantitative computed tomography QCT continues to advance its functional capabilities through dual-energy technology, novel magnetic resonance imaging techniques are being developed that offer the potential to further enhance ILD assessment.27
Quantification of lung involvement on HRTC is useful at different time in RA-ILD: at diagnosis, to define treatment and prognosis of patient, in follow up, to value the progression of disease and response to treatment, and in research trial.
The latter point is especially interesting due to recent availability of new agents supposed to be able to modifying RA-ILD course, as mycophenolate, biologic agents and antifibrosis drugs.28 To have reliable data on efficacy of treatments, it is important the accessibility of a reliable and reproduceable instrument of measurement of lung involvement.
Between visual scores, Goh scores is the most diffuse system, but are time-consuming, operator-dependent and need a specific training to be performed.
The Goh score has been validated and rheumatoid arthritis,29 and appears to be a suitable instrument for the quantification of RA-ILD. It is reasonable to presume that the Goh score might have a similar predictive value for mortality.9 On the other hand, QCT may be easily performed also by a physician not trained in radiology. QCT measurements have proven to provide highly accurate and reproducible diagnoses, although they require some level of training to follow a standardized imaging acquisition protocol. Moreover, fully automated QCT measurements could eliminate intra- and interobserver variability, a useful characteristic in a number of circumstances as diagnostic, patient management, multi-center assessment and multi-center trials.
The performance of QCTi has been previously explored in other autoimmune diseases such as systemic sclerosis (SSc) and Sjögren syndrome(SS). For instance, in a recent series by Ariani et al.,22 the authors reported a moderate-to-good agreement of all values for ILD associated with SSc, and also in cases with extensive or limited lung disease. Some pulmonary function tests also showed a relatively good correlation with QCT indices (FVC and DLco<70%). Our study present good correlation between visual semiquantitative scores and the majority of QCTi. As QTC appears able to distinguish between limited and extensive ILD, it is a reliable tool in prognosis evaluation. In RA, it was demonstrated that total involvement of lung parenchyma is associated with mortality, independently of radiologic pattern,30 tKurt appears the QTCi with the best discriminant capacity, with a cut-off value of 3.67. The study shows a partial correlation between QTc and functional indices, which would represent an advantage when assessing progression during follow-up of pharmacological treatment. According to our results, the associations between the quantitative parameters and QCT, FVC and DLco indices had both positive and negative correlation coefficients and, being calculated between 0.4 and 0.6, can be considered moderate; however, these associations could be clinically relevant, so studies require confirmation in studies with larger sample sizes.
This study is not without its weaknesses, some of the most important of which are: first, the fact that it is a retrospective study, so some data on the included patients are missing. Second, no clinical follow-up of the patients was performed to assess the progression of lung disease or the sensitivity of the technique and third, qualitative assessment was not performed, this was because it was beyond the scope of the article; and finally the sample size was discrete, which allowed us to see a trend in certain correlations of variables, which could be significant with a larger number of patients analyzed.
This methodology is unable to distinguish between different radiological patterns, and it has been shown that, in RA-ILD, the detection of a radiological pattern of usual interstitial pneumonia (UIP) is associated with limited survival. However, QTC indices could distinguish between high and low mortality groups31 in cases of ESC with ILD, in relation to clinical scales predicting 1-year mortality, such as the ILD-GAP score (ILD subtype, sex, age, FVC and DLco) or dBi (age, history of respiratory hospitalization and FVC value and its change at 6 months). Furthermore, computer analysis of CT data is theoretically capable of distinguishing different radiological patterns, but this application is still under-researched.
In summary, we demonstrated that, as in other CTD-related ILD, in RA-ILD, QCTi correlate with the sQCT. Our preliminary findings suggest that RA-ILD severity is related to QCTi. Moreover, there is a cutoff of one the QCTi (tKurt) that can discriminate very well patients with a severe ILD. Also, the operator-independent algorithm we used in this study is free and time-saving, so, this method might be extremely suitable for multi-center trials focused on ILD.
QCTi may become simple tools to help the rheumatologist to quickly evaluate the severity of ILD in RA patients and estimate the prognosis. We believe that this innovative tool will open new horizons for research into RA-ILD, as it has the capability to select ILD patients with extensive lung impairment and, correspondingly, a worse prognosis. We are confident that in the near future QCT will play pivotal role in the diagnosis, monitoring and treatment of ILD associated with RA as well as other CTD-related ILD.
FundingNone.
Conflict of interestNone of the authors have any potential conflicts of interest to disclose in relation to this work.
A. Ariani has received honoraria as a speaker and an advisory board member of Bristol-Myers Squibb, Novartis and Sanofi.




