



To validate, in routine clinical practice, the SER/SEPAR criteria for the screening of rheumatoid arthritis (RA)-associated interstitial lung disease (ILD).
MethodsA retrospective study was conducted in patients with RA who had undergone high-resolution computed tomography (HRCT) of the lungs within the past 5 years. Clinical and radiological variables were collected, and the proposed screening criteria were applied. Sensitivity and specificity of the overall algorithm, as well as of its individual components, were calculated.
ResultsA total of 270 patients were included (71% women), with a mean age of 64.3 years and a mean disease duration of 10.8 years. Among them, 58 patients (21.5%) had ILD on HRCT. Application of the SER/SEPAR criteria yielded a sensitivity of 96.5% and a specificity of 25%, recommending screening tests in 90% of patients and HRCT in 75% of them. The individual sensitivity of chest radiography and pulmonary function tests (PFTs) for the detection of ILD was low (≤50%) in both symptomatic and asymptomatic patients. The presence of lung crackles on lung auscultation was the finding with the highest specificity (92.9%).
ConclusionThe SER/SEPAR screening criteria show excellent sensitivity but low specificity, leading to the recommendation of diagnostic testing in the majority of patients. In our cohort, chest X-ray and PFTs demonstrated limited utility for ILD screening in patients with RA.
Validar en práctica clínica habitual los criterios SER/SEPAR para el cribado de enfermedad pulmonar intersticial difusa (EPID) asociada a artritis reumatoide (AR).
MétodoEstudio retrospectivo en pacientes con AR a los que se había realizado una tomografía computarizada de alta resolución (TCAR) de pulmón en los últimos 5 años. Se recogieron variables clínicas y radiológicas y se aplicaron los criterios de cribado propuestos. Se calculó la sensibilidad y especificidad del algoritmo en su conjunto, así como de las variables que lo forman.
ResultadosSe incluyeron 270 pacientes (71% mujeres) con una media de edad de 64,3 años y un tiempo medio de evolución de la AR de 10,8 años. De ellos, 58 pacientes (21,5%) presentaban EPID en la TCAR. Tras su aplicación, los criterios SER/SEPAR presentaron una sensibilidad del 96,5% y una especificidad del 25%, recomendando hacer pruebas de cribado en un 90% de los pacientes. En un 75% de ellos se recomendó realizar TCAR pulmonar.
La sensibilidad individual de la radiografía de tórax y de las pruebas de función respiratoria (PFR) fue baja para la detección de EPID (≤50%) tanto en pacientes sintomáticos como asintomáticos. La presencia de crepitantes en la auscultación pulmonar fue el hallazgo con mayor especificidad (92,9%).
ConclusiónLos criterios de cribado SER/SEPAR presentan una sensibilidad excelente, pero una baja especificidad, recomendando realizar pruebas diagnósticas en la mayoría de los pacientes. En nuestra cohorte, la radiografía de tórax y las PFR demostraron una baja utilidad para el cribado de EPID en pacientes con AR.
Diffuse interstitial lung disease (ILD) is a frequent and potentially severe complication in patients with rheumatoid arthritis (RA). Its prevalence has been estimated at between 5% and 57% according to different studies, and it is believed to be frequently underdiagnosed.1–4 Some recent works suggest an increase in its diagnosis, due to greater clinical awareness and the application of screening strategies.5 ILD is associated with an increase in morbidity and mortality, and currently constitutes the second cause of death among patients with RA, after cardiovascular events.2,6,7 High-resolution computed tomography (HRCT) is considered to be the “gold standard” to establish its diagnosis.
Although the prognosis of RA has improved significantly with the development of biological and targeted synthetic disease-modifying anti-rheumatic drugs (DMARDs), rheumatoid arthritis-associated interstitial lung disease (RA-ILD) remains one of the most severe complications of this disease. Given its impact on survival, early detection is crucial to improve the prognosis, and diagnostic delay has been associated with higher rates of mortality.8 The difficulty resides in the fact that, in its initial stages, RA-ILD can present subclinically. Therefore, it becomes necessary to establish adequate screening criteria to avoid late diagnoses, when therapeutic options become more limited and less effective.
Recently, the Spanish Society of Rheumatology (Sociedad Española de Reumatología or SER), in collaboration with the Spanish Society of Pulmonology and Thoracic Surgery (Sociedad Española de Neumología y Cirugía Torácica or SEPAR), have published recommendations for the management of RA-ILD9 and proposed screening criteria based on clinical data and risk factors.10 This proposal, aimed at all patients with RA, was developed via consensus of a panel of experts in Rheumatology and Pulmonology, following the Delphi methodology.
The objective of this study is to validate these criteria in routine clinical practice, in a large cohort of patients with RA, in order to determine their sensitivity, specificity and predictive values for the detection of ILD.
Materials and methodDesign of the studyThis was a single-centre retrospective study aiming to validate a screening test in routine clinical practice, using the “gold standard” as reference.
PatientsThe study included all patients aged between 18 and 90 years, with an established diagnosis of RA (EULAR/ACR 2010 criteria) treated at the Rheumatology Department of Ramón y Cajal University Hospital in Madrid (Spain), who had undergone a lung HRCT scan in routine clinical practice between 1 January 2020 and 31 December 2024. The reason for requesting the HRCT scan was clinical suspicion of ILD or the presence of respiratory symptoms (acute or chronic dyspnoea, cough, expectoration, chest pain or fever). The study only considered patients in whom the HRCT scan was conducted following the protocol for pulmonary interstitial assessment (supine position, during inspiration, with thin slices [≤1.5 mm] and using high-frequency reconstruction filters). In all cases, the Radiology Department determined the presence or absence of radiological findings of ILD in the lung HRCT scan and this result was considered as the “gold standard” to validate the criteria.
The study excluded patients with a prior diagnosis of RA-ILD or ILD of any other aetiology, as well as those with a history of thoracic surgery or radiotherapy that might modify the imaging tests. In addition, patients with a lung HRCT scan carried out in the 2 years prior were also excluded, as were those in whom HRCT was conducted during acute SARS-CoV-2 infection.
The study included patients with RA, regardless of disease duration, clinical manifestations and any previous or current treatment they were receiving.
The study was approved by the local Ethics Committee and all patients signed an informed consent form.
VariablesThe clinical, analytical, radiological and monitoring variables were registered for all patients. Specifically, the variables registered were those included in the ILD screening recommendations of SER/SEPAR: age, sex, duration of RA, serum levels of rheumatoid factor and anti-citrullinated peptide antibodies, smoking, moderate-to-high RA activity, family history of ILD, presence of “Velcro-type” crackles during lung auscultation, and presence of cough and/or dyspnoea with a duration longer than 3 months. All the variables were collected taking into account the date when the HRCT scan was carried out for each patient.
In addition, the results of a chest X-ray (conducted up to 6 months before HRCT) were registered, as were pulmonary function tests (PFTs), which included forced vital capacity (FVC) and diffusing capacity for carbon monoxide (DLCO), expressed as a percentage of predicted value, conducted in the 6 months before or after HRCT.
The ILD screening criteria proposed by SER/SEPAR were applied to each patient and the results obtained were recorded: a) indication to perform diagnostic tests, and b) indication to perform a lung HRCT scan.
The main variables of the study were the sensitivity and specificity of the recommendation to perform HRCT to reach a diagnosis of ILD.
Statistical analysisA descriptive analysis of the variables was conducted. Quantitative variables were expressed as mean and standard deviation, while qualitative variables were described as absolute frequencies and percentages.
The overall sensitivity and specificity of the criteria were calculated and, subsequently, individually for the different variables comprising them (crackles, cough and/or dyspnoea, scoring scale), as well as for the complementary tests. Contingency tables and percentages were employed for qualitative variables. For the scoring scale, a ROC analysis was conducted and the area under the curve (AUC) was calculated. Lastly, the sensitivity and specificity of chest radiography and PFTs for the diagnosis of ILD in symptomatic patients were calculated.
All the statistical analyses were conducted using the software program SPSS v25.
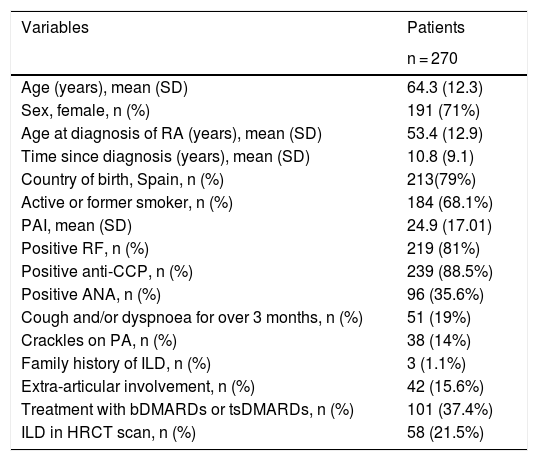
ResultsA total of 270 patients with RA were included in the study. The mean age was 64.3 years and 191 (71%) were female. The mean duration of RA was 10.8 years. In total, 45% of patients were former smokers and 23% were active smokers at the time of HRCT. Rheumatoid factor was positive in 81% of patients and anti-citrullinated peptide antibody (anti-CCP) was positive in 88%. Out of the 270 patients, 58 (21.5%) had ILD confirmed by the HRCT scan. The remaining general characteristics of the patients at the time of inclusion are detailed in Table 1.
Sociodemographic, clinical and analytical variables of the patients at the time of performing thoracic HRCT.
| Variables | Patients |
|---|---|
| n = 270 | |
| Age (years), mean (SD) | 64.3 (12.3) |
| Sex, female, n (%) | 191 (71%) |
| Age at diagnosis of RA (years), mean (SD) | 53.4 (12.9) |
| Time since diagnosis (years), mean (SD) | 10.8 (9.1) |
| Country of birth, Spain, n (%) | 213(79%) |
| Active or former smoker, n (%) | 184 (68.1%) |
| PAI, mean (SD) | 24.9 (17.01) |
| Positive RF, n (%) | 219 (81%) |
| Positive anti-CCP, n (%) | 239 (88.5%) |
| Positive ANA, n (%) | 96 (35.6%) |
| Cough and/or dyspnoea for over 3 months, n (%) | 51 (19%) |
| Crackles on PA, n (%) | 38 (14%) |
| Family history of ILD, n (%) | 3 (1.1%) |
| Extra-articular involvement, n (%) | 42 (15.6%) |
| Treatment with bDMARDs or tsDMARDs, n (%) | 101 (37.4%) |
| ILD in HRCT scan, n (%) | 58 (21.5%) |
ANA: antinuclear antibodies; anti-CCP: anti-cyclic citrullinated peptide antibodies; bDMARDs: biological DMARDs; DMARDs: disease-modifying anti-rheumatic drugs; HRCT: high-resolution computed axial tomography scan; ILD: diffuse interstitial lung disease; PA: pulmonary auscultation; PAI: pack-year index in smokers and former smokers; RA: rheumatoid arthritis; RF: rheumatoid factor; SD: standard deviation; tsDMARDs: targeted synthetic DMARDs.
Extra-articular involvement: presence of rheumatoid nodules, serositis, Sjögren’s syndrome, Felty’s syndrome, vasculitis, or ophthalmological involvement.
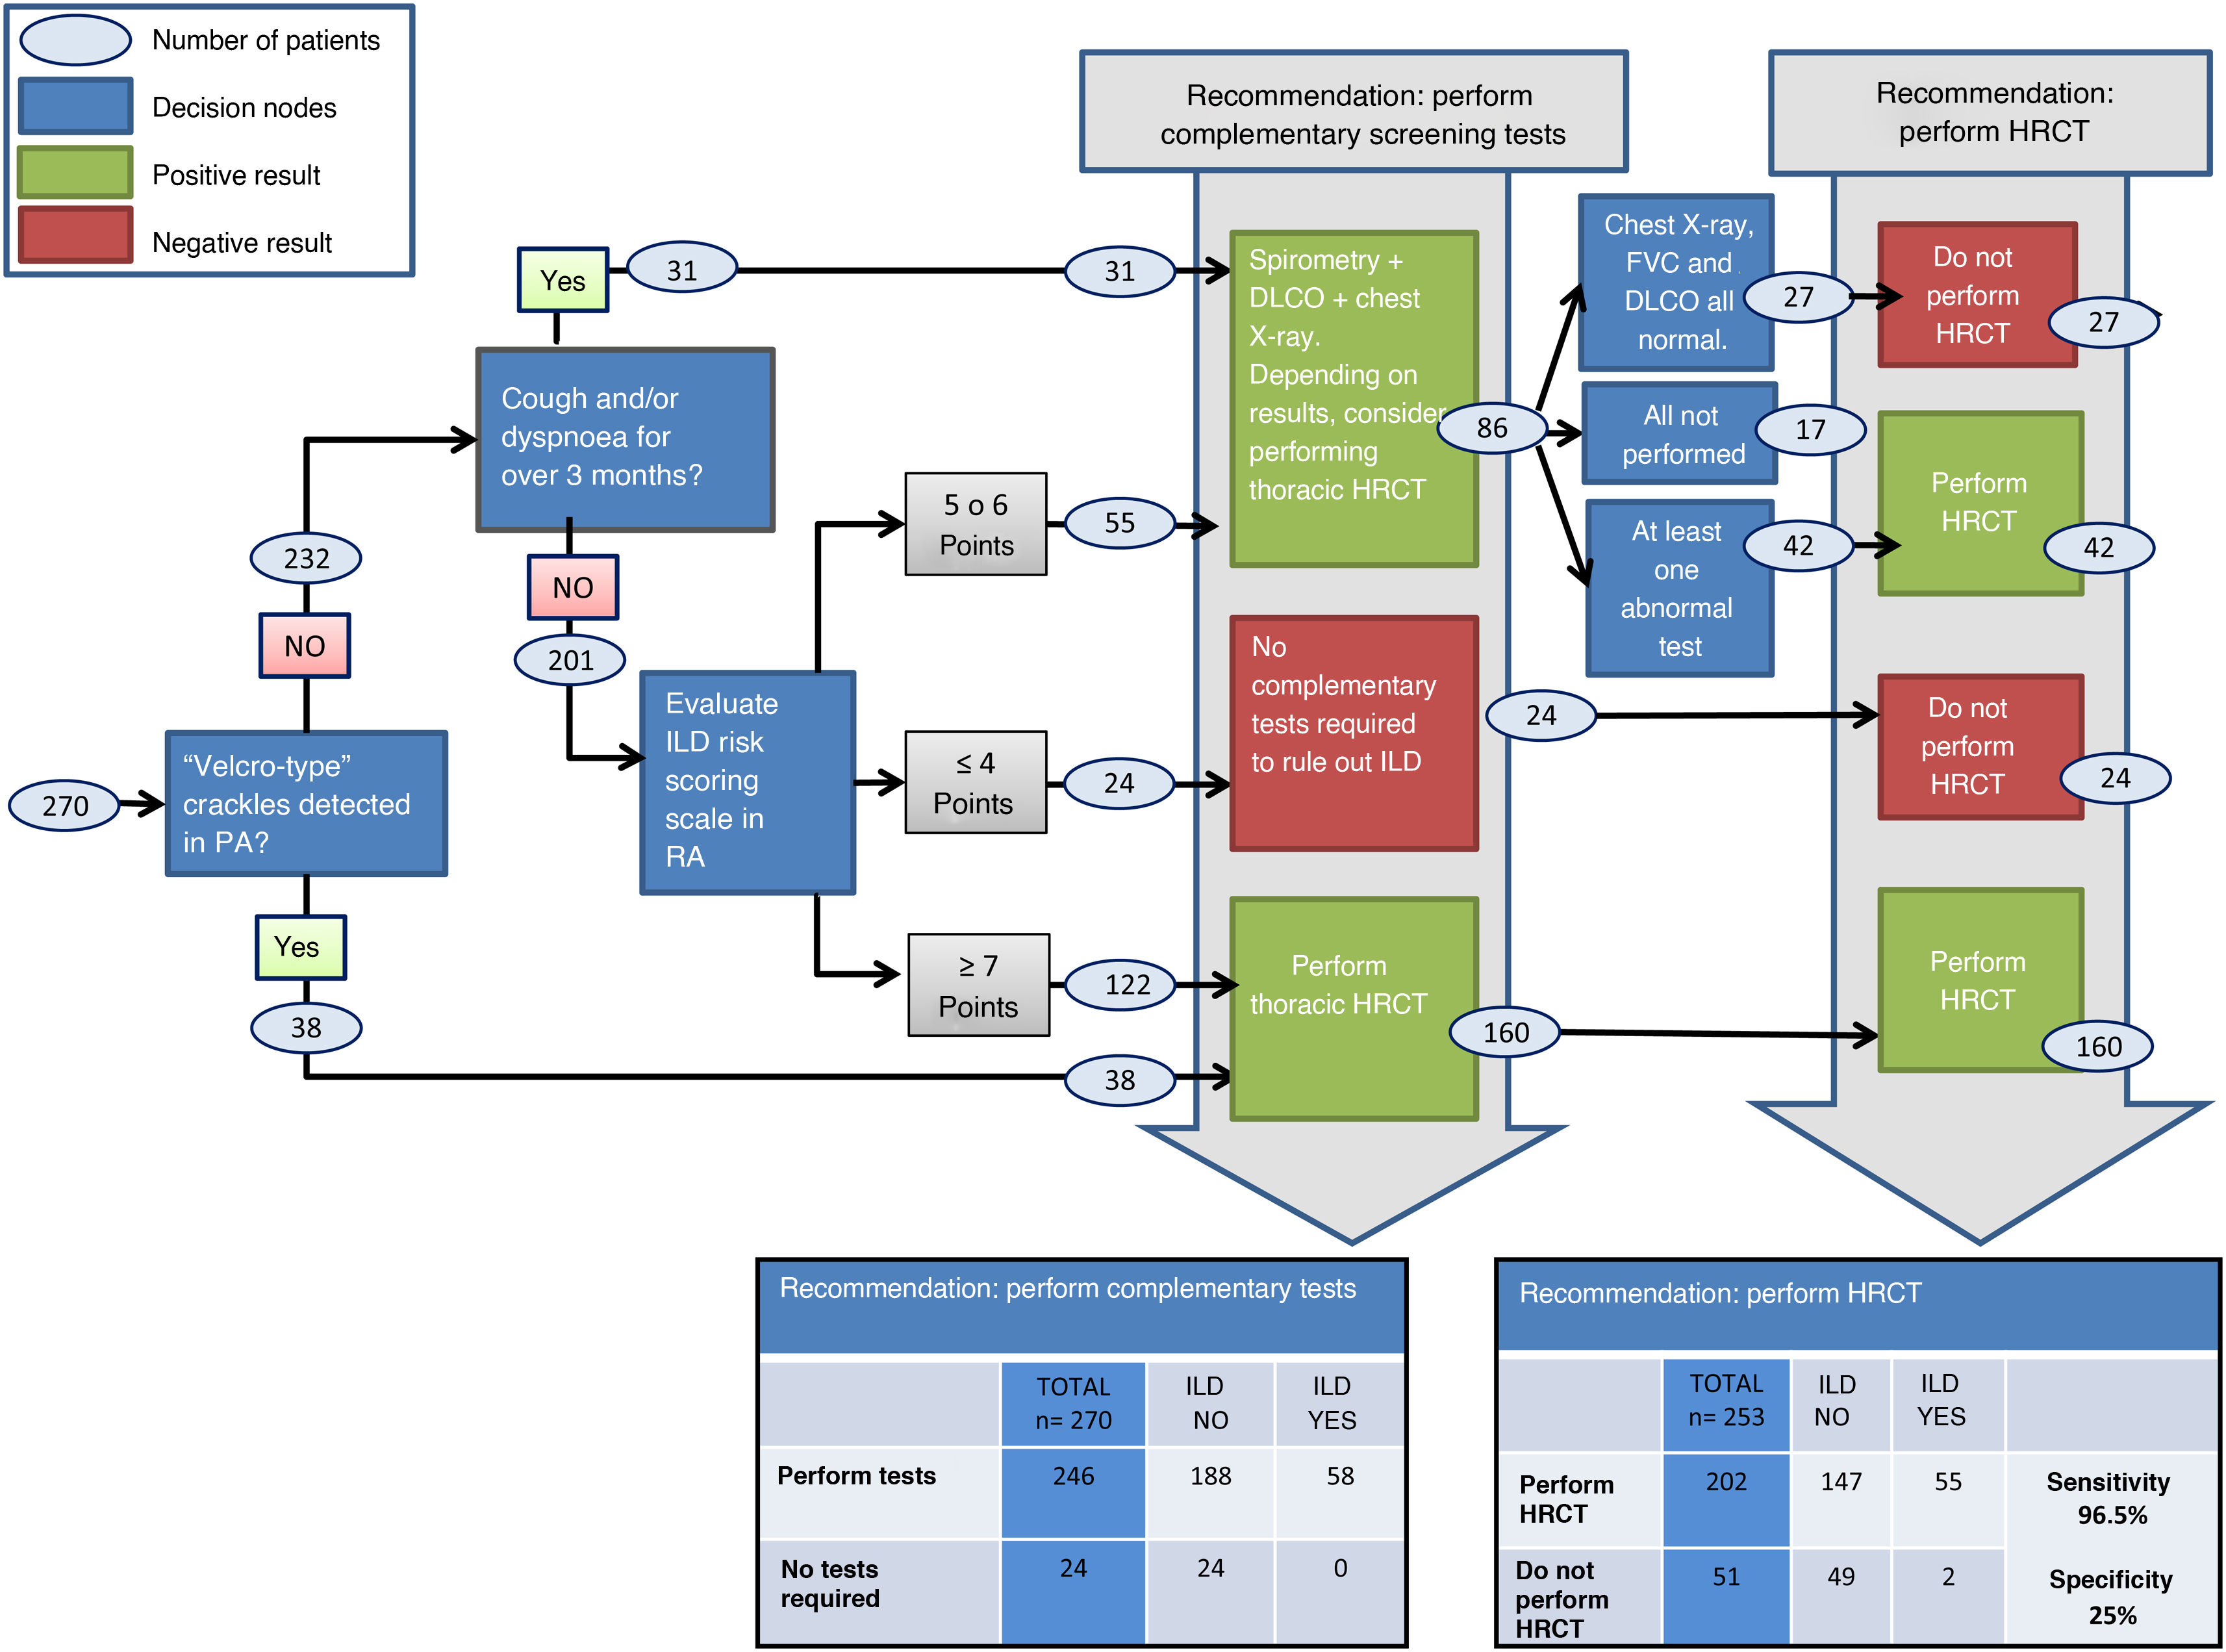
In the total cohort, 18 patients presented with crackles on lung auscultation, 31 had clinical symptoms of cough and/or dyspnoea lasting longer than 3 months, and 20 presented with both manifestations. The median score according to the proposed scale was 7 (range: 2–11; interquartile range: 6–9). The distribution of patients into the different subgroups according to the scenarios (decision nodes) of the SER/SEPAR screening criteria is shown in Fig. 1.

Distribution of patients in the validation cohort, based on the ILD screening criteria proposed by SER-SEPAR.
The number of patients is shown according to decision nodes, and the sensitivity and specificity results of the criteria regarding the recommendation to “Perform HRCT.”
In blue square: decision nodes. In blue circle: number of patients in each group. In green square: perform tests. In red square: do not perform tests.
DLCO: diffusing capacity of lungs for carbon monoxide adjusted by haemoglobin; FVC: forced vital capacity; HRCT: high resolution computed axial tomography scan; ILD: diffuse interstitial lung disease; PA: pulmonary auscultation; RA: rheumatoid arthritis.
For 246 patients (91.1%), the SER/SEPAR criteria recommended performing diagnostic tests to screen for ILD: in 160 patients the recommendation was to perform lung HRCT directly, while in 86 patients it was to perform chest X-ray, FVC and DLCO (Fig. 1). After evaluating the results of these latter tests (these 3 diagnostic tests were not available for 17 patients), the indication to perform HRCT was established in a total of 202 patients (74.8%). The sensitivity of the SER/SEPAR criteria for the diagnosis of ILD (recommendation to perform HRCT) was 96.5%, and the specificity was 25% (Fig. 1), with a positive predictive value of 27.2% and negative predictive value of 96.1%.
If the cut-off point in the scoring scale for “does not require complementary tests” in the screening criteria was modified from ≤4 points to ≤5 points, the overall results barely improved their diagnostic utility (sensitivity: 94.7%; specificity: 28.5%). With a cut-off point of ≤6 points, the sensitivity became 89.6% and specificity 36.4%. On the other hand, if chest X-ray and pulmonary function tests were no longer used as a screening method, and instead a pulmonary HRCT scan was conducted on all symptomatic patients (“Velcro-type” crackles and/or cough or dyspnoea for over 3 months), as well as those with a score ≥5 points, then the sensitivity of the criteria became 100% and the specificity 11.3%.
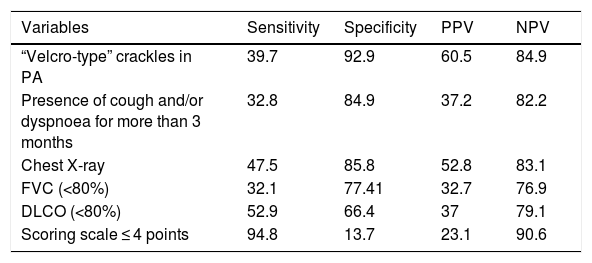
The individual analysis of sensitivity and specificity for each variable comprising the SER/SEPAR criteria is presented in Table 2. Clinical variables (crackles in lung auscultation and presence of cough and/or dyspnoea) showed low sensitivity and moderate-high specificity. On the other hand, the risk scoring scale with the proposed cut-off point (≥5 points) had a sensitivity of 95%, with a specificity below 15%. The individual sensitivity of chest X-ray and PFTs was low, around 50% (Table 2).
Diagnostic validity of the variables used to construct the SER/SEPAR criteria, analysed individually across the entire validation cohort.
| Variables | Sensitivity | Specificity | PPV | NPV |
|---|---|---|---|---|
| “Velcro-type” crackles in PA | 39.7 | 92.9 | 60.5 | 84.9 |
| Presence of cough and/or dyspnoea for more than 3 months | 32.8 | 84.9 | 37.2 | 82.2 |
| Chest X-ray | 47.5 | 85.8 | 52.8 | 83.1 |
| FVC (<80%) | 32.1 | 77.41 | 32.7 | 76.9 |
| DLCO (<80%) | 52.9 | 66.4 | 37 | 79.1 |
| Scoring scale ≤ 4 points | 94.8 | 13.7 | 23.1 | 90.6 |
| Variables | Area under the curve |
|---|---|
| Scoring scale | 0.616 |
DLCO: percentage capacity of lungs for carbon monoxide adjusted by haemoglobin relative to predicted value; FVC: percentage of forced vital capacity relative to predicted value; NPV: negative predictive value; PA: pulmonary auscultation; PPV: positive predictive value.
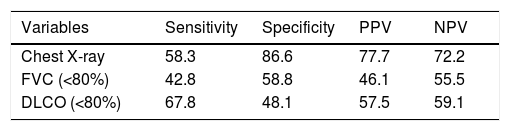
In the analysis conducted only on the 69 symptomatic patients (Table 3), chest radiography, FVC and DLCO continued to show low sensitivities for a diagnosis of ILD (58%, 43% and 68%, respectively).
Sensitivity and specificity of the diagnostic tests used to detect ILD in symptomatic patients (patients with “Velcro-type” crackles in PA and/or presence of cough and/or dyspnoea for more than 3 months).
| Variables | Sensitivity | Specificity | PPV | NPV |
|---|---|---|---|---|
| Chest X-ray | 58.3 | 86.6 | 77.7 | 72.2 |
| FVC (<80%) | 42.8 | 58.8 | 46.1 | 55.5 |
| DLCO (<80%) | 67.8 | 48.1 | 57.5 | 59.1 |
DLCO: percentage capacity of lungs for carbon monoxide adjusted by haemoglobin relative to predicted value; FVC: percentage of forced vital capacity relative to predicted value; ILD: diffuse interstitial lung disease; NPV: negative predictive value; PA: pulmonary auscultation; PPV: positive predictive value.
This retrospective study validated the screening algorithm for RA-ILD proposed jointly by the SER and SEPAR societies10 under routine clinical practice conditions. The results show that the algorithm has a very high sensitivity (96.5% of patients with ILD would be diagnosed by applying the criteria), albeit at the expense of a low specificity. This translates into a high rate of indication for diagnostic tests (90%), specifically HRCT (75%) in the studied cohort, although with a very high negative predictive value.
These findings reinforce the usefulness of the SER/SEPAR algorithm as a sensitive tool to avoid omitting cases of ILD, especially in environments where early detection is essential. Nevertheless, the low specificity of the algorithm could limit its applicability in environments with a lower access to complementary tests, such as HRCT, leading to a potentially excessive use of diagnostic resources.
The detection and management of ILD in cases of inflammatory rheumatic diseases is a key issue which has motivated multiple reviews and recommendations by scientific societies and working groups in recent years. So far, general screening recommendations11–14 and simple risk score scales15,16 have been published in regards to RA, but there is no common consensus among the different initiatives. The proposal by SER/SEPAR is the only systematic evaluation strategy to include a structured and risk-based decision algorithm. These criteria constitute a firm commitment to providing rheumatologists with a practical and easily applied tool for RA-ILD screening. In our study, the SER/SEPAR criteria were applied rigorously, according to the original proposal, allowing faithful validation under real practice conditions.
Another work validating these SER/SEPAR criteria has been published recently,17 but it is limited only to patients with early RA (duration of symptoms ≤12 months). This study, also retrospective and conducted at a single-centre, describes a prevalence of RA-ILD of 19.2%, similar to that found in our own cohort (21%). With regard to the criteria validation results, the authors also found a very high sensitivity and low specificity.17 One significant methodological difference is that this work did not perform HRCT on all patients, but only on those who fulfilled the screening criteria, so the prevalence of ILD could be underestimated and the reported sensitivity and specificity results of the criteria could vary. In addition, this study included patients who had already been diagnosed with ILD, whereas our own cohort excluded those cases, and also patients who had undergone a lung HRCT scan in the previous 2 years (even when result was negative). This strict selection of patients increases the clinical validity of our results.
Another interesting aspect of our work is the analysis of the individual utility of each variable included in the criteria. It is worth noting that, in our study, neither chest radiography nor pulmonary function tests (FVC, DLCO) showed the necessary sensitivity to detect ILD, even among symptomatic patients. These findings are consistent with those reported by other studies, which point out the low diagnostic yield of chest radiography for the early detection of subclinical ILD.18,19 In fact, the latest ACR/CHEST guidelines for the detection and monitoring of ILD,11 as well as other works,14 do not recommend chest radiography for screening. There is greater discrepancy in the results of PFTs.18,20 DLCO is more sensitive than FVC18 and could be useful in cases with marked reductions (≈50%),21 but the 2023 ACR/CHEST guidelines recommend using HRCT and PFTs instead of conducting PFTs exclusively for screening.11
The presence of crackles on lung auscultation was the clinical finding with the highest specificity (92.9%), although with a limited sensitivity. This highlights the value of detailed physical exploration as a key element of the algorithm, although it was not sufficient to guide diagnostic decisions by itself. Furthermore, the risk scoring scale proposed by SER/SEPAR showed a high sensitivity, but with little capacity to discriminate, as shown in our ROC analysis. Moreover, modifying the cut-off points did not improve the results significantly. Other score scales based on clinical characteristics published recently,15,16 have performed similarly. It would be necessary to assess the relative weight of each variable included, in order to develop a new scoring scale with higher specificity.
The proposed screening algorithm includes a decision node that may be incongruent and on which the panel did not reach a common consensus.10 Among patients who presented with cough or dyspnoea, the recommendation is to conduct a chest X-ray and/or PFTs, followed by a lung HRCT scan according to the result. However, some of these patients had ≥7 points on the risk scale, so if they did not present with respiratory symptoms they would proceed directly to the indication to perform HRCT. This aspect could classify some of the patients erroneously, delaying the diagnosis and contributing to the low overall specificity of the criteria.
Other factors and tools with a potential to improve the early detection of ILD include biomarkers, such as matrix metalloproteinases,22,23 polymorphisms in the MUC5B gene,24 and emerging imaging techniques like lung ultrasound.25,26 In the future, these techniques will enable the sensitivity and specificity of screenings to be improved.
Among the limitations of this study it is worth noting its retrospective nature and the possible selection of patients with a higher clinical suspicion of ILD. This could have led to an overestimation of the prevalence of ILD and the sensitivity of the algorithm. Moreover, being a single-centre study could have introduced a patient selection bias. Although the number of rheumatologists who included patients was high, it could be that the recruited cohort did not reflect the diversity of clinical practices and profiles of patients found at other hospitals and regions. On the other hand, the assessment of radiological findings and complementary tests by a single medical team should have reduced variability in the interpretation of these tests.
In conclusion, the SER/SEPAR criteria for ILD screening in RA showed an excellent sensitivity in clinical practice, and are useful to ensure early detection. However, their low specificity entails a high rate of test indications, which could limit their applicability in certain healthcare environments. Chest radiography demonstrated low diagnostic utility in this context. A future optimisation of the algorithm should include an improvement of decision nodes, a specific assessment of the clinical variables included, the incorporation of other biomarkers, and the use of new imaging tools, like lung ultrasound.
FinancingThe present study did not receive specific support from public, private or non-profit entities.
The authors have no conflict of interests to declare in regard to this work.




