



In the diagnosis and management of idiopathic inflammatory myopathies, cutaneous manifestations are particularly significant. Clinical signs are often associated with specific autoantibodies and play a role in the classification, treatment, and prognosis of IIM.
ObjectiveDescribe the cutaneous clinical presentation, phototype, and autoantibody profiles among Hispanic patients with IIM.
MethodsA cross-sectional study was conducted from January 2015 to November 2022, including 64 patients diagnosed with IIM. Rheumatological and dermatological evaluations were performed, assessing Fitzpatrick phototype and Cutaneous Dermatomyositis Activity and Severity Index (CDASI) scores. Autoantibodies were analyzed using immunoblotting.
ResultsDermatomyositis (DM) was the most common subtype (73.4%). Fitzpatrick phototypes IV (59.4%) and III (37.5%) predominated. CDASI scores indicated mild dermatological activity in 60.9% of cases. Cluster analysis identified four patient groups with distinct clinical and serological profiles.
ConclusionIIM have a complex disease expression. Recognizing its heterogeneities can enhance personalized treatment approaches.
En el diagnóstico y manejo de las miopatías inflamatorias idiopáticas las manifestaciones cutáneas son de particular importancia. Los signos clínicos suelen asociarse con autoanticuerpos específicos y desempeñan un papel en su clasificación, tratamiento y pronóstico.
ObjetivoDescribir la presentación clínica cutánea, el fototipo y los perfiles de autoanticuerpos entre pacientes hispanos con miopatía inflamatoria.
MétodosSe realizó un estudio transversal de enero de 2015 a noviembre de 2022, que incluyó 64 pacientes con diagnóstico de miopatía inflamatoria. Se efectuaron evaluaciones reumatológicas y dermatológicas, determinando el fototipo de Fitzpatrick y el puntaje del Cutaneous Dermatomyositis Activity and Severity Index (CDASI). Los autoanticuerpos se analizaron mediante inmunoblot.
ResultadosLa dermatomiositis fue el subtipo más frecuente (73.4%). Predominaron los fototipos IV (59.4%) y III (37.5%) de Fitzpatrick. Los puntajes de CDASI indicaron actividad dermatológica leve en el 60.9% de los casos. El análisis de conglomerados identificó cuatro grupos de pacientes con perfiles clínicos y serológicos distintos.
ConclusiónLas miopatías inflamatorias presentan una expresión clínica compleja. Reconocer sus heterogeneidades puede favorecer un abordaje más personalizado.
Idiopathic inflammatory myopathies (IIM) are rare systemic autoimmune diseases with an incidence of 1–19 cases per million annually.1 It is characterized by muscle inflammation leading to weakness and potential multi-organ involvement, commonly affecting systems like the skin, joints, gastrointestinal tract, heart, and lungs.2
Dermatomyositis (DM), immune-mediated necrotizing myopathy, overlap myositis (including antisynthetase syndrome), sporadic inclusion-body myositis, and polymyositis (PM) are among the most recognized and common types of IIM. They are associated with unique pathological and serological profiles.2,3
The prevalence and clinical implications of autoantibodies vary geographically. This seems to be influenced by latitude, suggesting that environmental factors, including ultraviolet (UV) radiation, are involved in disease manifestations.4,5 In addition, UV radiation exposure affects skin morphology and its ability to adapt to sunlight. The Fitzpatrick scale classifies skin phototypes based on their UV response, primarily determined by genetic variations in melanin production. Phototypes significantly influence cutaneous manifestations, including disease presentation.6
In the diagnosis and management of IIM, cutaneous manifestations are particularly significant; for instance, DM is distinguished by hallmark skin features, such as heliotrope rash, Gottron's papules, V-neck sign, and shawl sign. These clinical signs are often associated with specific autoantibodies and play a role in classification, treatment, and prognosis of IIM.7 In IIM, cutaneous activity often correlates with disease severity and prognosis yet the relationship between skin phototypes, specific cutaneous features, and the presence of autoantibodies in autoimmune myopathy panels remains scarcely studied. This study aims to describe the phototype, cutaneous activity, and autoantibody profiles in IIM patients from a Hispanic population.
Materials and methodsStudy design and populationThis observational cross-sectional study included patients aged ≥18 years diagnosed with inflammatory myopathy according to the Bohan and Peter 1975 criteria within five years of disease onset, from January 2015 to November 2022, and who attended our institution. Exclusion criteria included overlap syndromes and incomplete clinical data.
Clinical and dermatological assessmentA single dermatologist evaluated the phototype using the Fitzpatrick classification1–6 and classified dermatological lesions using the CDASI scale as: remission (<5), low activity,5–19 and severe activity (>19). CDASI was reported as activity score and damage score. The dermatologist was blinded to diagnosis, antibodies, and therapeutics. Rheumatologists assessed muscle involvement, and other organ involvement (pulmonary, gastrointestinal).
Autoantibodies testingAutoantibody profiles were analyzed using immunoblot techniques targeting 17 markers: Mi-2α, Mi-2β, TIF1-γ, MDA5, NXP2, SAE1, Ku, PM/Scl-75, PM/Scl-100, Jo-1, SRP, PL-7, PL-12, EJ, OJ, Ro52, cN1A.
The study was approved by the Institutional Review Board with the register number RE22-00002.
Statistical analysisDescriptive statistics summarized patient demographics and clinical characteristics. Principal component analysis (PCA) was conducted to reduce dimensionality. Cluster analysis was performed using the k-means method based on gender, age, diagnosis, phototype, CDASI scores, and autoantibody profiles. Comparisons across clusters are descriptive and were not adjusted for disease duration or concomitant immunosuppressive/biologic therapy. Statistical analyses were conducted in R Studio and SPSS v25 (IBM, Armonk, NY, USA).
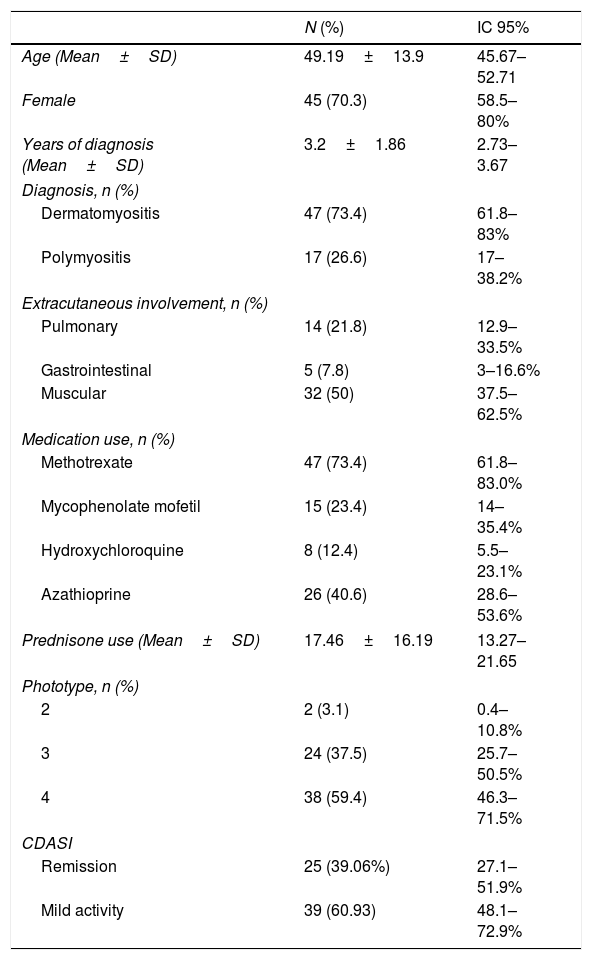
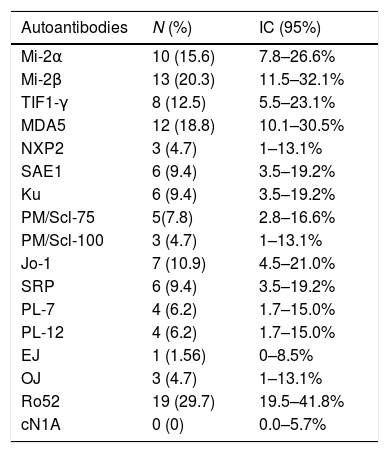
ResultsWe included 64 patients (70% female) with a mean age of 49 (SD 13.6). Dermatomyositis was the most common subtype (73.4%). Muscle involvement was reported in 63.9% of patients, and pulmonary involvement in 45.9%. Phototype IV was the most prevalent (59.4%), followed by phototype III (37.5%). CDASI scores indicated mild cutaneous activity in 60.9% of patients, with 39.1% in remission (Table 1). Autoantibody prevalence is shown in Table 2.
General characteristics.
| N (%) | IC 95% | |
|---|---|---|
| Age (Mean±SD) | 49.19±13.9 | 45.67–52.71 |
| Female | 45 (70.3) | 58.5–80% |
| Years of diagnosis (Mean±SD) | 3.2±1.86 | 2.73–3.67 |
| Diagnosis, n (%) | ||
| Dermatomyositis | 47 (73.4) | 61.8–83% |
| Polymyositis | 17 (26.6) | 17–38.2% |
| Extracutaneous involvement, n (%) | ||
| Pulmonary | 14 (21.8) | 12.9–33.5% |
| Gastrointestinal | 5 (7.8) | 3–16.6% |
| Muscular | 32 (50) | 37.5–62.5% |
| Medication use, n (%) | ||
| Methotrexate | 47 (73.4) | 61.8–83.0% |
| Mycophenolate mofetil | 15 (23.4) | 14–35.4% |
| Hydroxychloroquine | 8 (12.4) | 5.5–23.1% |
| Azathioprine | 26 (40.6) | 28.6–53.6% |
| Prednisone use (Mean±SD) | 17.46±16.19 | 13.27–21.65 |
| Phototype, n (%) | ||
| 2 | 2 (3.1) | 0.4–10.8% |
| 3 | 24 (37.5) | 25.7–50.5% |
| 4 | 38 (59.4) | 46.3–71.5% |
| CDASI | ||
| Remission | 25 (39.06%) | 27.1–51.9% |
| Mild activity | 39 (60.93) | 48.1–72.9% |
Antibodies prevalence.
| Autoantibodies | N (%) | IC (95%) |
|---|---|---|
| Mi-2α | 10 (15.6) | 7.8–26.6% |
| Mi-2β | 13 (20.3) | 11.5–32.1% |
| TIF1-γ | 8 (12.5) | 5.5–23.1% |
| MDA5 | 12 (18.8) | 10.1–30.5% |
| NXP2 | 3 (4.7) | 1–13.1% |
| SAE1 | 6 (9.4) | 3.5–19.2% |
| Ku | 6 (9.4) | 3.5–19.2% |
| PM/Scl-75 | 5(7.8) | 2.8–16.6% |
| PM/Scl-100 | 3 (4.7) | 1–13.1% |
| Jo-1 | 7 (10.9) | 4.5–21.0% |
| SRP | 6 (9.4) | 3.5–19.2% |
| PL-7 | 4 (6.2) | 1.7–15.0% |
| PL-12 | 4 (6.2) | 1.7–15.0% |
| EJ | 1 (1.56) | 0–8.5% |
| OJ | 3 (4.7) | 1–13.1% |
| Ro52 | 19 (29.7) | 19.5–41.8% |
| cN1A | 0 (0) | 0.0–5.7% |
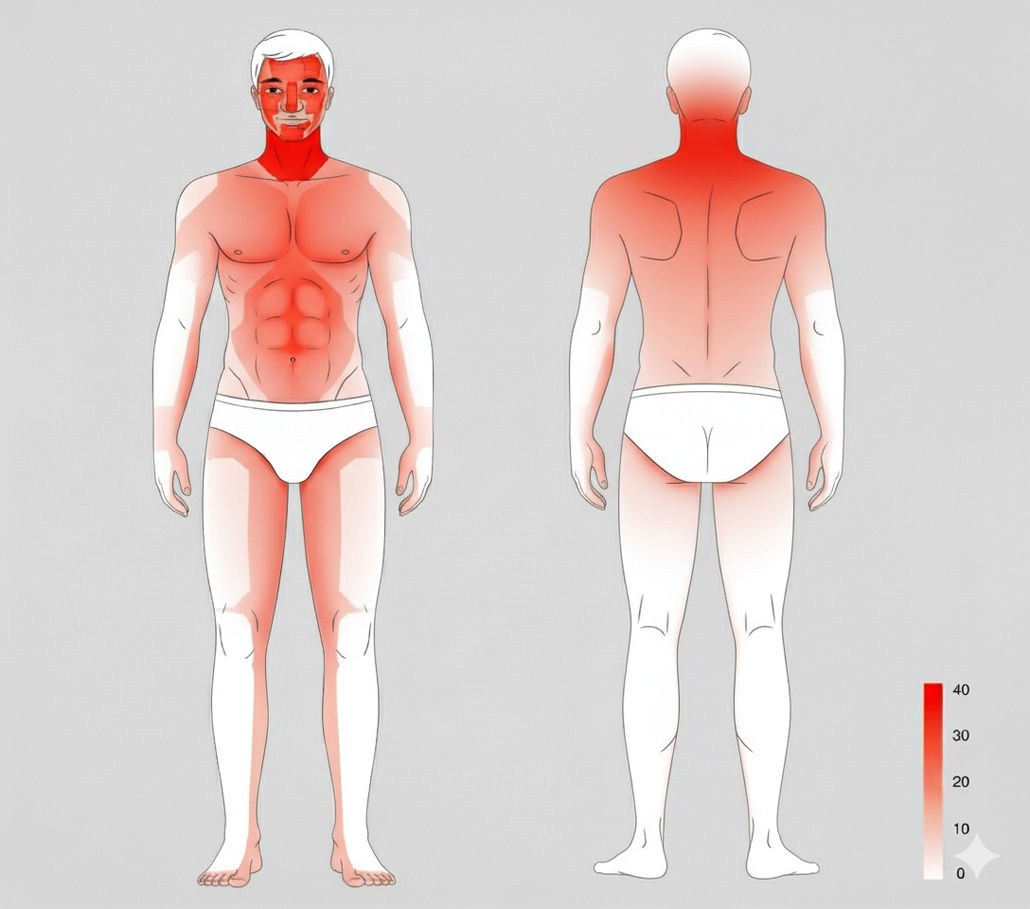
Erythema prevalence by anatomic region is shown in Fig. 1. Poikiloderma was present in 46 (71.87%) patients, most frequently observed in the V-area of the neck (46.88%), upper back and shoulders (34.38%), and the arms (42.19%). Gottron's papules and Gottron's sign were observed in 43.75% and 39.06% of patients, respectively. Over half of the patients (65.62%) exhibited periungual microscopic telangiectasias, and 3 (4.68%) had visible telangiectasias. One-fifth of the patients presented with mechanic hands. Erosions (3 patients) and calcinosis (1 patient) were rare.

PCA was deemed inappropriate (KMO=0.43).
ClustersThe variability in the data as indicated by the sum of squares was: 2384.44, 5604.25, 2104.80, and 1453.87 for each cluster respectively. The explained between-cluster variance made up 65.8% of the total variance.
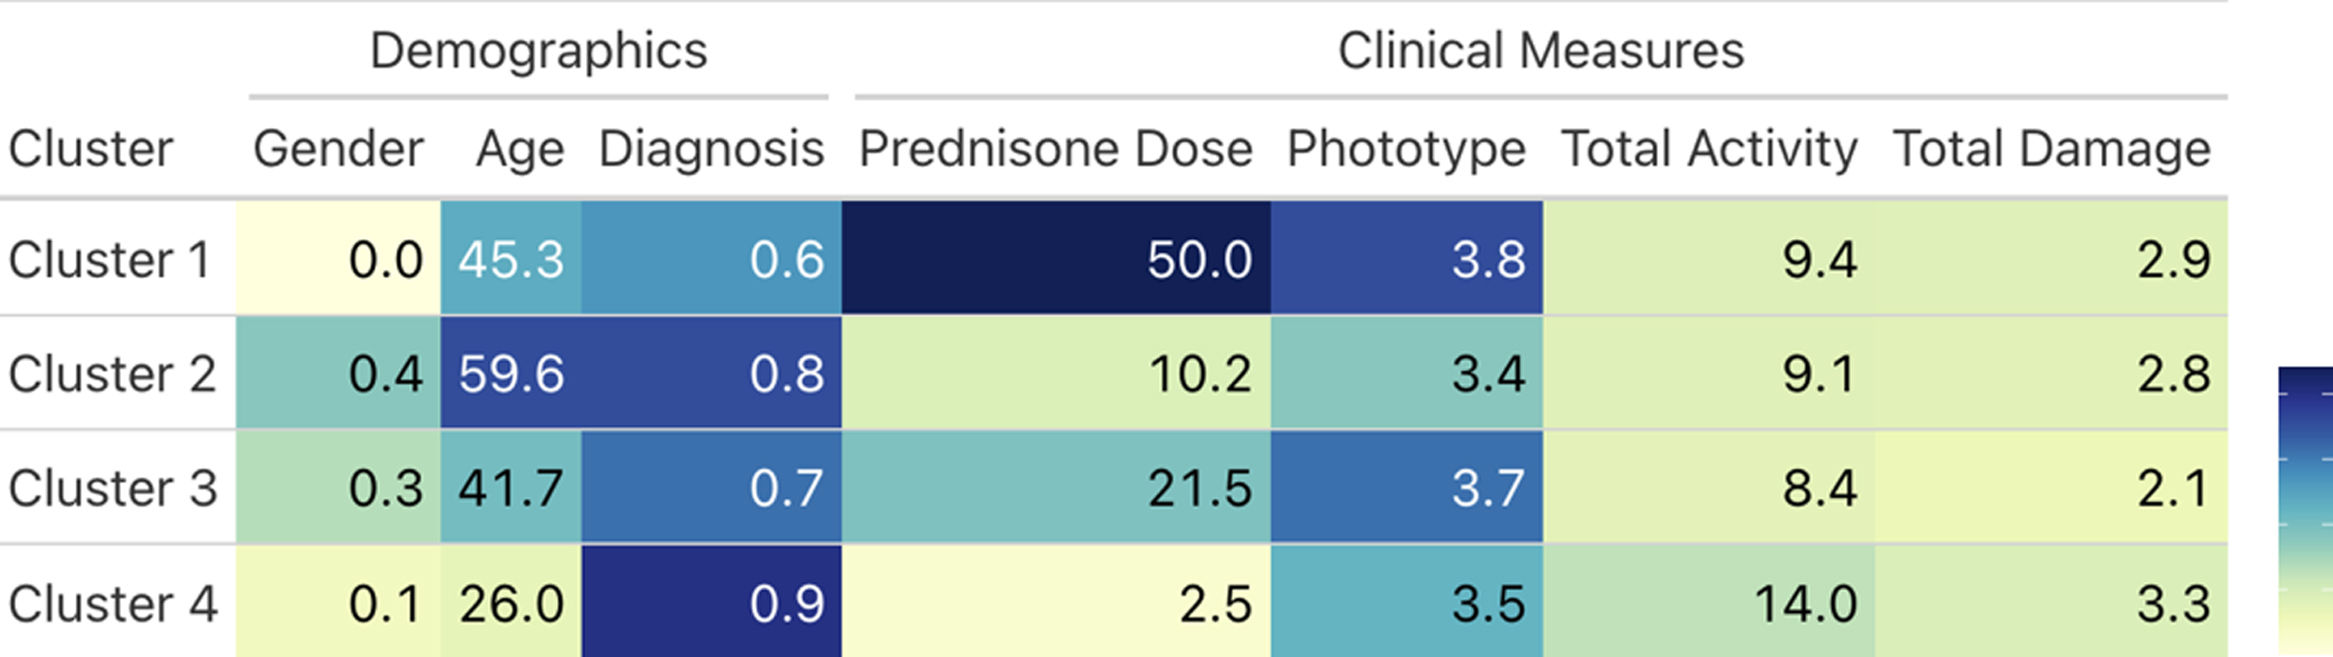
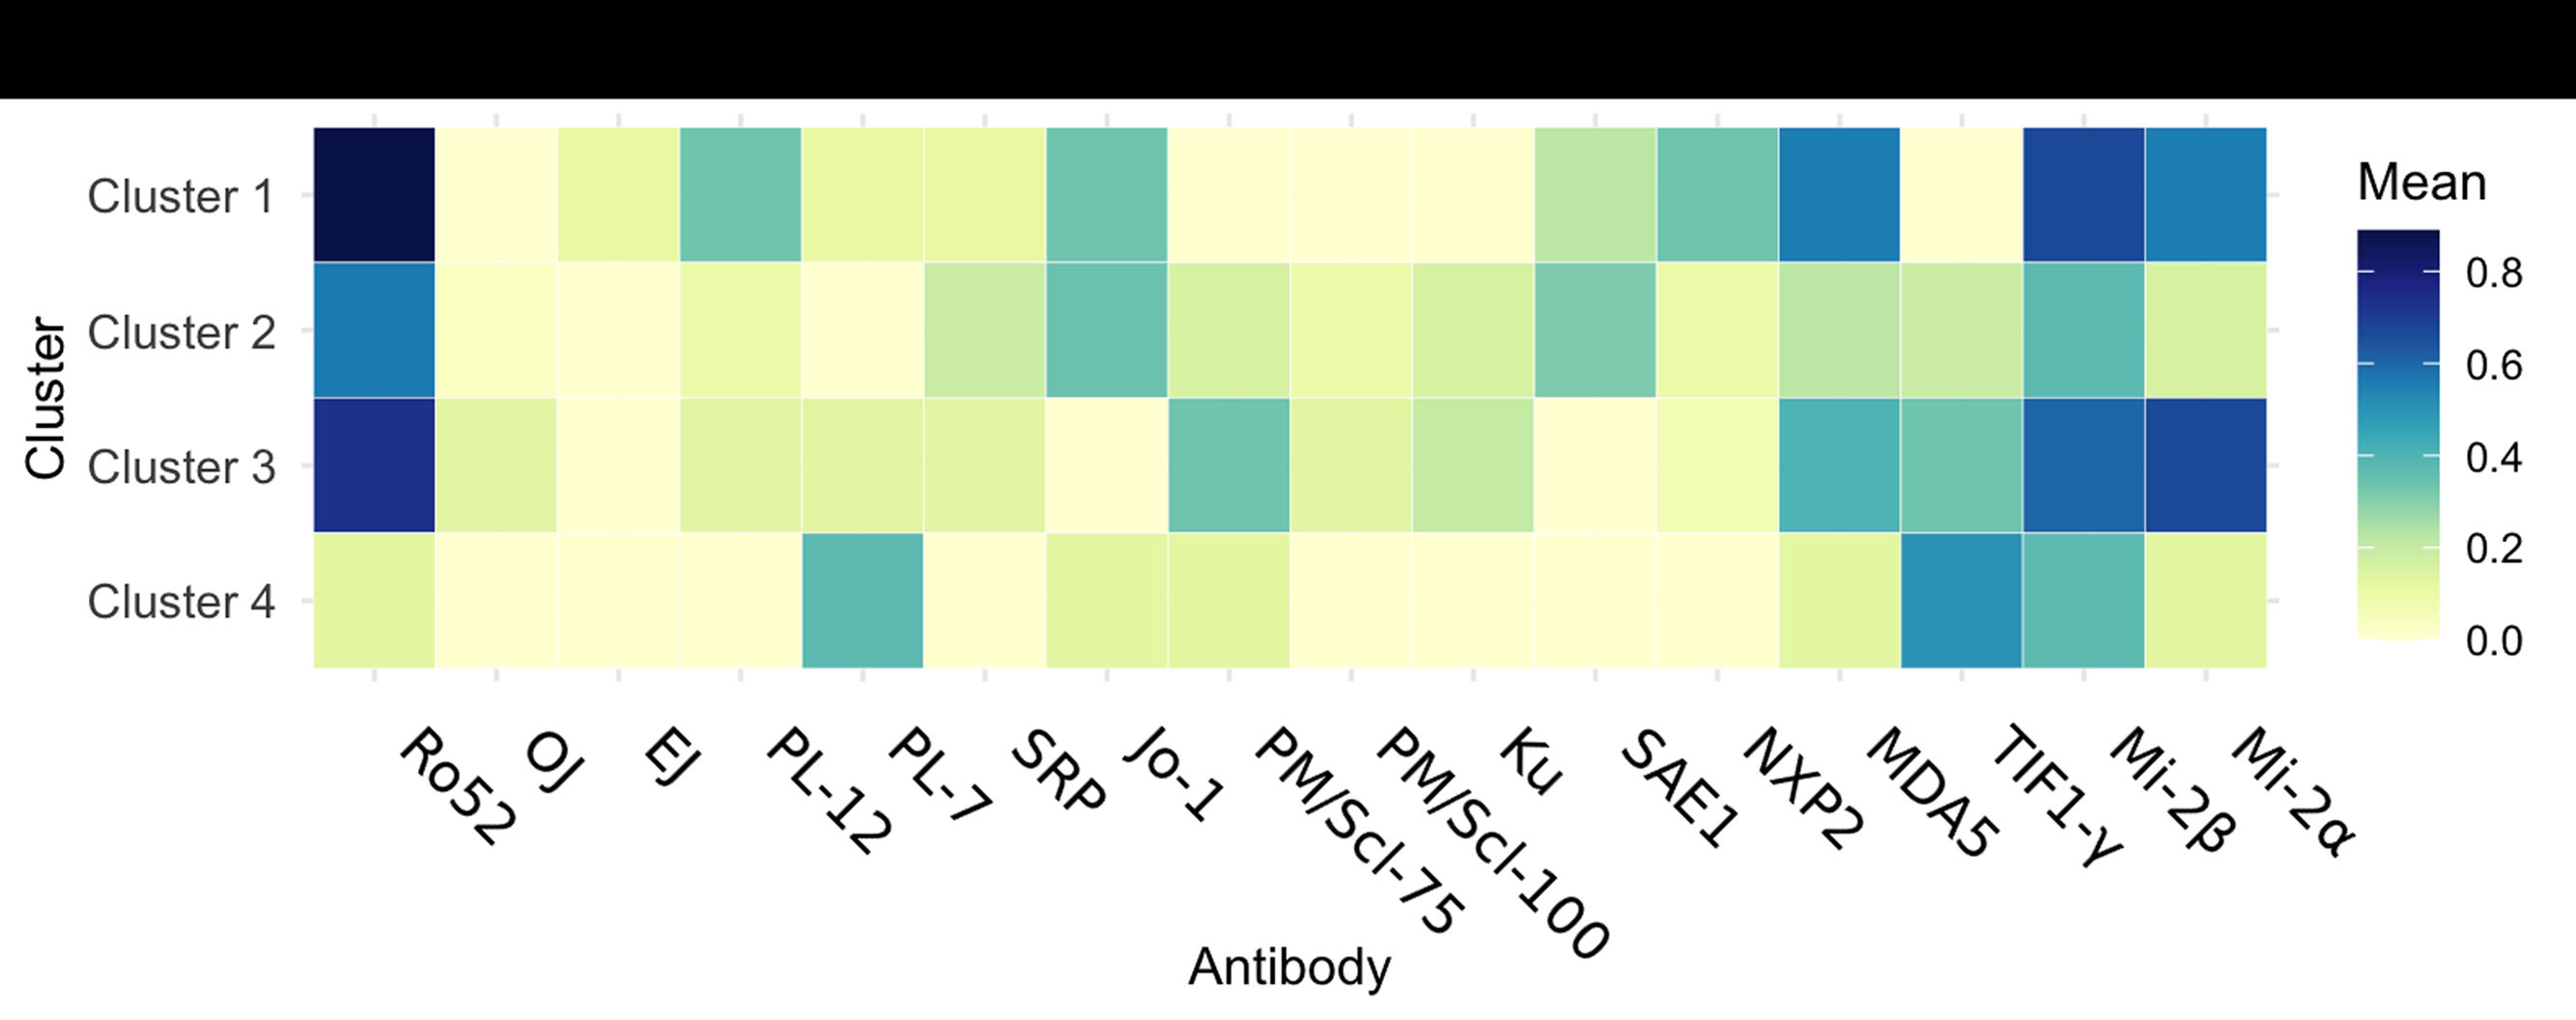
Cluster 1 (n=9) was exclusively female, with a mean age of 45.3 years, and the highest proportion of PM. This cluster was treated with the highest prednisone dose (50mg) at the time of assessment. It showed moderate CDASI activity (9.44) and CDASI damage (2.89). Serologically, there was noticeable presence of Ro52, and elevated values for Mi-2β and Mi-2α.
Cluster 2 (n=32) showed the highest proportion of men (41%) and the highest mean age (59.6 years). They were managed with a lower prednisone dose (10.16mg). Overall activity (9.09) and damage (2.81) were similar to those in Cluster 1. The serological markers were lower, but the most remarkable when compared to other clusters were OJ, SRP, Jo-1, and SAE1.
Cluster 3 (n=15) had a predominantly female composition and a mean age of 41.7 years. Prednisone dose (21.5mg) was intermediate, with slightly lower overall activity (8.40) and damage (2.07) compared to Clusters 1 and 2. OJ, PM/Scl-75, PM/Scl-100, Ku and Mi-2α were most prevalent in this cluster.
Cluster 4 (n=8) was almost exclusively females, characterized by the younger patient group with a mean age of 26 years. It had the highest proportion of DM. These patients received the lowest prednisone dose (2.50mg), and they showed the highest overall activity (14.00) and damage (3.25) scores among all clusters. Serologically, most autoantibodies were not present, the most predominant were TIF1-γ and PL-7.
Phototype distribution was similar among clusters. General characteristics distribution across clusters presents in Fig. 2 and antibodies in Fig. 3.

Clinical variables by cluster. Each variable was scaled to facilitate comparability across different measures. Gender was coded as 0 for women and 1 for men. Age was scaled from 18 to 70 years. Diagnosis was represented as 0 for polymyositis and 1 for dermatomyositis. Prednisone dose ranged from 0 to 50. Phototype was scaled from 3 to 4. Total activity was scaled from 0 to 50, while total damage ranged from 0 to 16.

Exploring the cutaneous manifestations of infrequent disorders like IIM in populations often overlooked in the literature can help recognize these conditions across underrepresented patient populations. Cutaneous lesions can show variability depending on skin phototype, which is closely related to skin pigmentation and UV response.6,8 Accordingly, we aimed to describe the cutaneous clinical presentation, Fitzpatrick phototype distribution, and autoantibody profiles in our Hispanic IIM cohort. Given the importance of skin manifestations for the diagnosis of IIM, we describe cutaneous manifestations observed in our population, which mostly includes phototype III or IV patients. This distribution likely reflects the demographic composition of the population served by our center.
Heliotrope erythema and Gottron's papules are among the most frequent features of DM. In our study, these signs were present in nearly half of the patients. Poikiloderma was the most common skin manifestation in our study. It is typically found on the upper chest, but in our population, it was most commonly observed on the posterior neck. Clinical differences across populations have been previously described, such as lower rates of Gottron's sign and higher rates of mechanic's hands in Hispanic patients compared to non-Hispanic.9,10
Higher phototypes also exhibit their own dermatological features. For instance, skin dyschromia (particularly hyperpigmentation) is more pronounced, rather than the usual erythematous or violaceous patches and plaques seen in lighter skin phototypes.11 In patients with darker skin tones, findings such as heliotrope rash and Gottron's papules, may not be as pronounced and may appear as darker or hyperpigmented lesions, making them less recognizable.12 Other recently described examples in Hispanic population include the sunburn sign characterized by bright red erythema on facial bony prominences, and the suntan sign characterized by a brownish-gray hyperpigmentation with soft desquamation that seems to be the aftermath of the sunburn sign.13
Moreover, the CDASI activity score has been mostly validated in white patients.14 Therefore, CDASI-based comparisons should be interpreted cautiously, particularly in cohorts with higher phototypes. Additionally, these patients often present diagnostic challenges in recognizing dermatologic conditions due to the subtler presentation of signs like erythema, leading to longer diagnostic times.15,16 These variations underscore the need for tailored diagnostics. Future work may explore artificial intelligence–assisted educational tools to improve recognition of IIM-related skin findings across a range of skin tones. In this context, augmented reality-based filters that overlay visual cues have shown promising results in improving learner confidence when identifying dermatologic findings on diverse skin tones.17
We should also consider the prevalence of autoantibodies according to population. Geographical latitude influences the prevalence of IIM autoantibodies, possibly resulting from a unique gene-environment interaction including different pathogeneses, a combination of genetic factors, and environmental triggers.18,19 The prevalence of autoantibodies like Mi-2, PL-12, Ro52, PM/Scl-75, Ku increases closer to the Equator, while NXP2 and aminoacyl-tRNA synthetase (ARS) autoantibodies show higher prevalence farther from the Equator.20 In European countries Jo-1 is the most prevalent autoantibody20 and is the only autoantibody included among the EULAR/ACR classification criteria for IIM.21 In regions like ours, where Jo-1 prevalence appears lower, this underscores the importance of considering geographic variability in autoantibody distributions when interpreting serological patterns.
Specific autoantibodies have been described and are very useful biomarkers for diagnosis and prognosis of these diseases.22 Their association with distinct clinical profiles has been well documented. For instance, Jo-1 is linked to antisynthetase syndrome, characterized by myopathy, interstitial lung disease, arthritis, and Raynaud phenomenon. Mi-2 is a classic marker for DM and is associated with a favorable response to steroid treatment and a good prognosis. In contrast, SRP is related to necrotizing myopathy, often resistant to treatment. MDA5 relates to amyopathic DM and rapidly progressive interstitial lung disease, whereas TIF1-γ is frequently detected in DM cases related to malignancy.23–25 The four clusters identified in our study, had different CDASI activity and serological characteristics. Cluster 1 showed the highest prednisone dose at the time of assessment and the highest presence of Ro52 and MI-2. Cluster 2 had the highest proportion of male patients and older age was characterized by Jo-1 and SAE1. Cluster 3 showed an intermediate disease profile and had notable levels of PM/Scl-75, MDA5, and TIF1-γ. Finally, Cluster 4, the youngest group had the highest disease activity and damage scores, and the highest prevalence of TIF1-γ and PL-7, reflecting a phenotype with severe cutaneous involvement. These findings reinforce the role of autoantibodies in defining clinical subsets within IIM and suggest that cutaneous disease severity (CDASI activity/damage) may vary across serological profiles in Hispanic patients with DM and PM. However, the applicability of the concept that a specific autoantibody directly determines a particular clinical manifestation remains uncertain. While associations have been observed, individual variability suggests that additional genetic, environmental, and immunological factors influence disease expression.
LimitationsThis study has some limitations. The sample size was relatively small, which may limit the generalizability of our findings. Additionally, the lack of longitudinal follow-up restricts our ability to assess the long-term implications of the identified clusters. The representation of phototypes was also limited, which may not fully capture the diversity of cutaneous manifestations across different skin tones. Furthermore, disease duration and treatment history (including concomitant immunosuppressive or biologic therapy) were not systematically captured. Therefore, prednisone dose and observed CDASI activity/damage may be influenced by unmeasured confounding. Finally, because our analyses primarily reflect the cutaneous domain, extracutaneous involvement was recorded as a binary variable, and systemic disease activity was not assessed using validated instruments.
ConclusionOur findings highlight the diversity of clinical and serological presentations in Hispanic patients with idiopathic inflammatory myopathies. The identification of four distinct clusters provides insight into how gender, age, phototype, autoantibody profiles, and disease activity could interplay in defining subgroups within this population. The complexity of disease expression leaves the need for a multifaceted approach to classification. Recognizing these heterogeneities can enhance personalized treatment approaches and refine prognostic predictions. Considering that cluster findings were exploratory, future multicenter, longitudinal studies with larger sample sizes are needed to validate these clusters and assess their stability across Hispanic populations.
Ethical standardsThis study was performed in accordance with the Declaration of Helsinki and was approved by the Institutional Review Board with the register number RE22-00002. All patients gave their informed consent prior to their inclusion in the study.
FundingThis research received no specific grant from any funding agency, commercial entity, or not-for-profit organization.
Conflict of interestsThe authors declare no conflicts of interest related to this work.
None.




